Regulatory Design Strategy for Medication Administration
Leading design for medication administration within Nourish's care record, whilst respecting strict regulatory boundaries.
- Organisation
- Nourish Care
- Project period
- 2025 — Present
- Disciplines
-
- Clinical safety
- Flow mapping
- Interaction design
- Prototyping

In brief
- The problem
- Medication rounds are high-stakes and frequent, and recording them apart from the care record loses context when it matters most. Some features would also tip the product into medical-device regulation.
- My role
- I led design with a Product Manager and our Clinical Safety Officer. I set the regulatory boundary, then designed the flows, the chart and the prototype myself.
- What changed
- A feature list became a model for managing risk: what the system supports, and where clinical judgement stays with people.
- Outcome
- A regulation-safe scope with clinical safety first, ready for research and testing with fuller prototypes.
Context
Medication administration is one of the highest-stakes, highest-frequency moments in social care, and the tools for recording it have historically sat apart from the rest of a person's care record. When that happens, care workers lose context at exactly the moment they need it most - and closing that gap is what this work is about.
My role
I led design on this work alongside a Product Manager and our Clinical Safety Officer, defining the regulatory boundary it needed to operate within, and then designing the flows, the chart and the prototype myself.
Constraints
This doesn't come with typical design freedom. Certain features (automated interaction checks, allergy alerts that make a clinical judgement, dose calculators) would push the product into medical device classification under UK regulation. There's a real line between software that supports a human decision and software that makes one, and everything we designed had to stay on the supporting side of it.
What we did
Discovery
Rather than starting from an assumed feature list, we ran structured discovery across several customer types. That meant sitting with the actual moment of medication administration as it happens today, and mapping the whole chain - how a medication decision gets made, prescribed, dispensed and finally given - along with everywhere it breaks down or loses information.
Journey mapping the administration round was the most valuable exercise by far. Laid out end to end, it showed how much of the risk sits in handovers; the information often exists somewhere in the system, just not in front of the care worker when they need it. So we stopped designing a single linear medication journey and made closing that handover gap the core problem.
Mapping every outcome
Before drawing a single chart, I mapped every way a dose can be recorded, whether it was given in full, in part or not at all. Each outcome has its own follow-up questions and ends in a confirmed log.
 (opens full size in a new tab)
If none of the dose was given, the care worker records why, and if only part of it was given, they record how. A refusal is always saved with a reason, so the MAR is never left with a blank cell.
When a care worker counts stock, the chart asks for their count before showing the expected number. Seeing the expected number first anchors people to it, so they end up confirming what they're shown rather than actually checking.
Structure before content
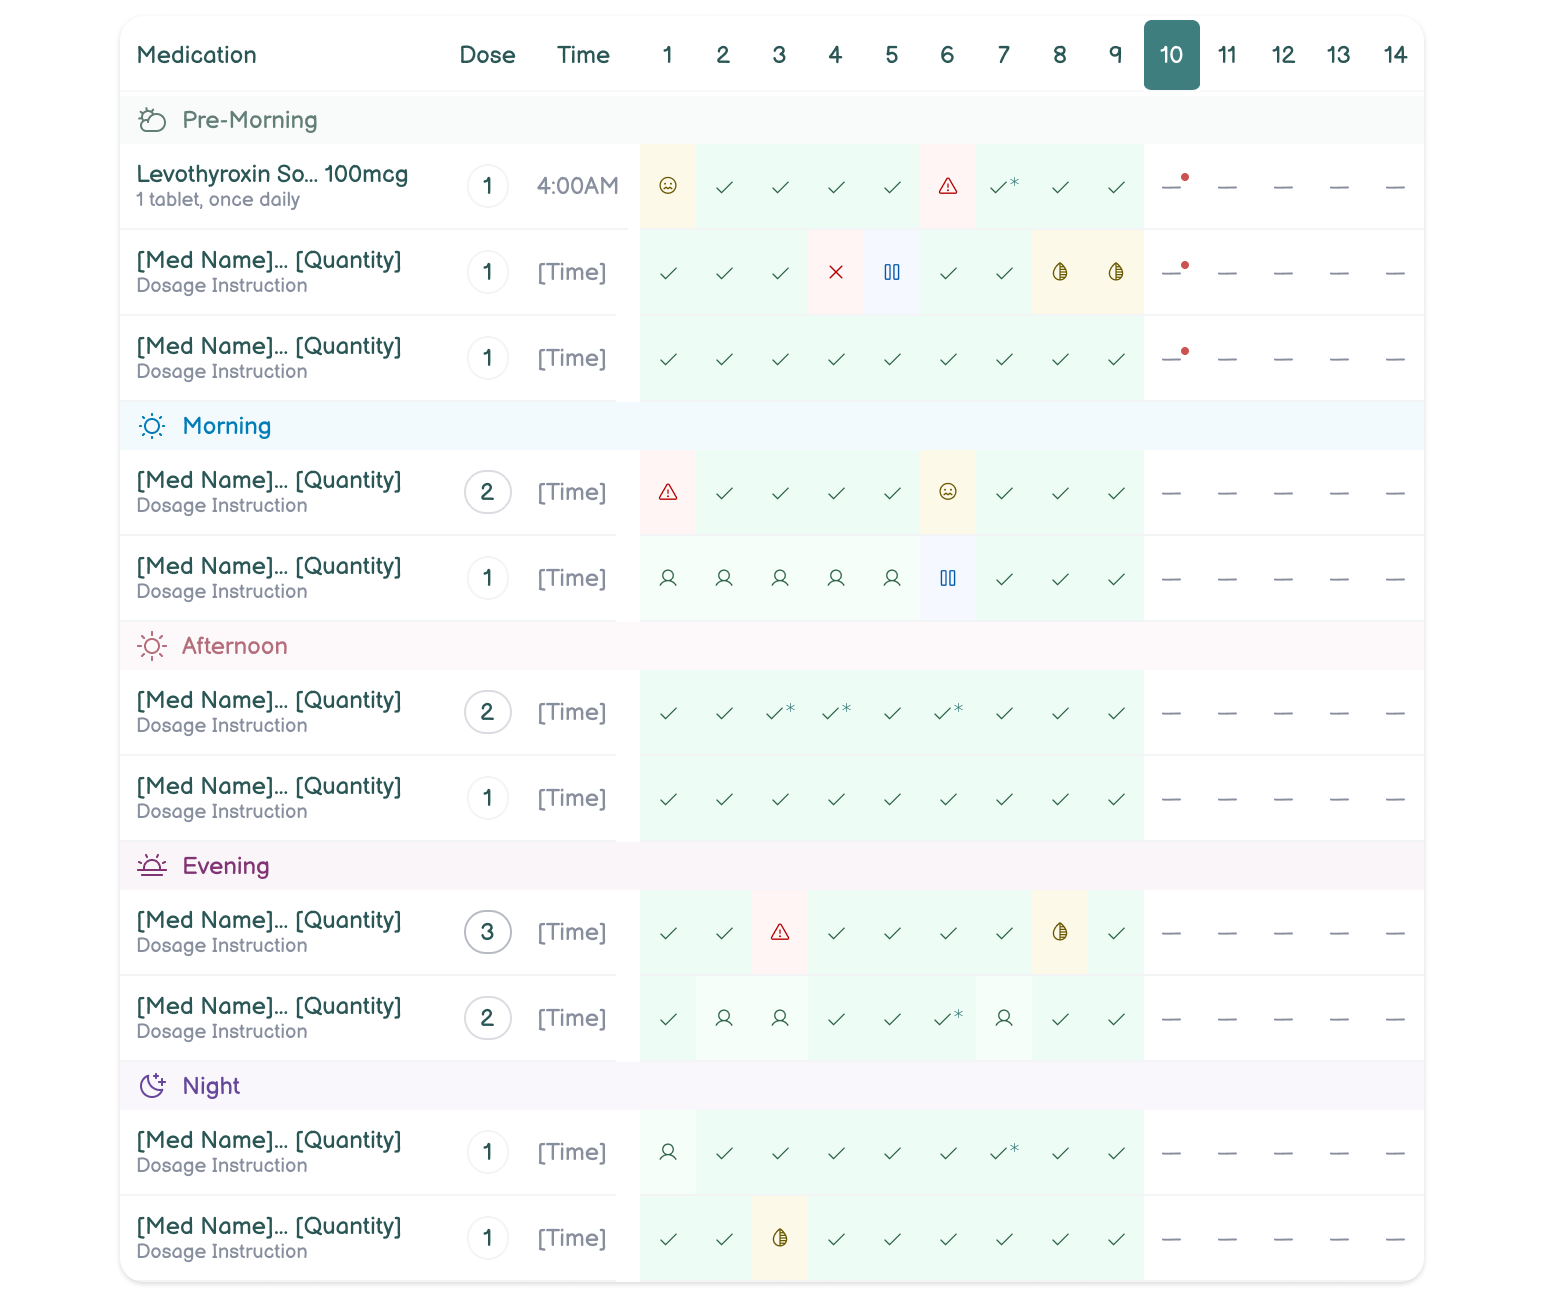
The first charts used placeholders for every medication, dose and time, so we could get the grid working (time of day, days of the week, one row per medication) before any realistic data went in.
 (opens full size in a new tab)
Status that doesn't rely on colour
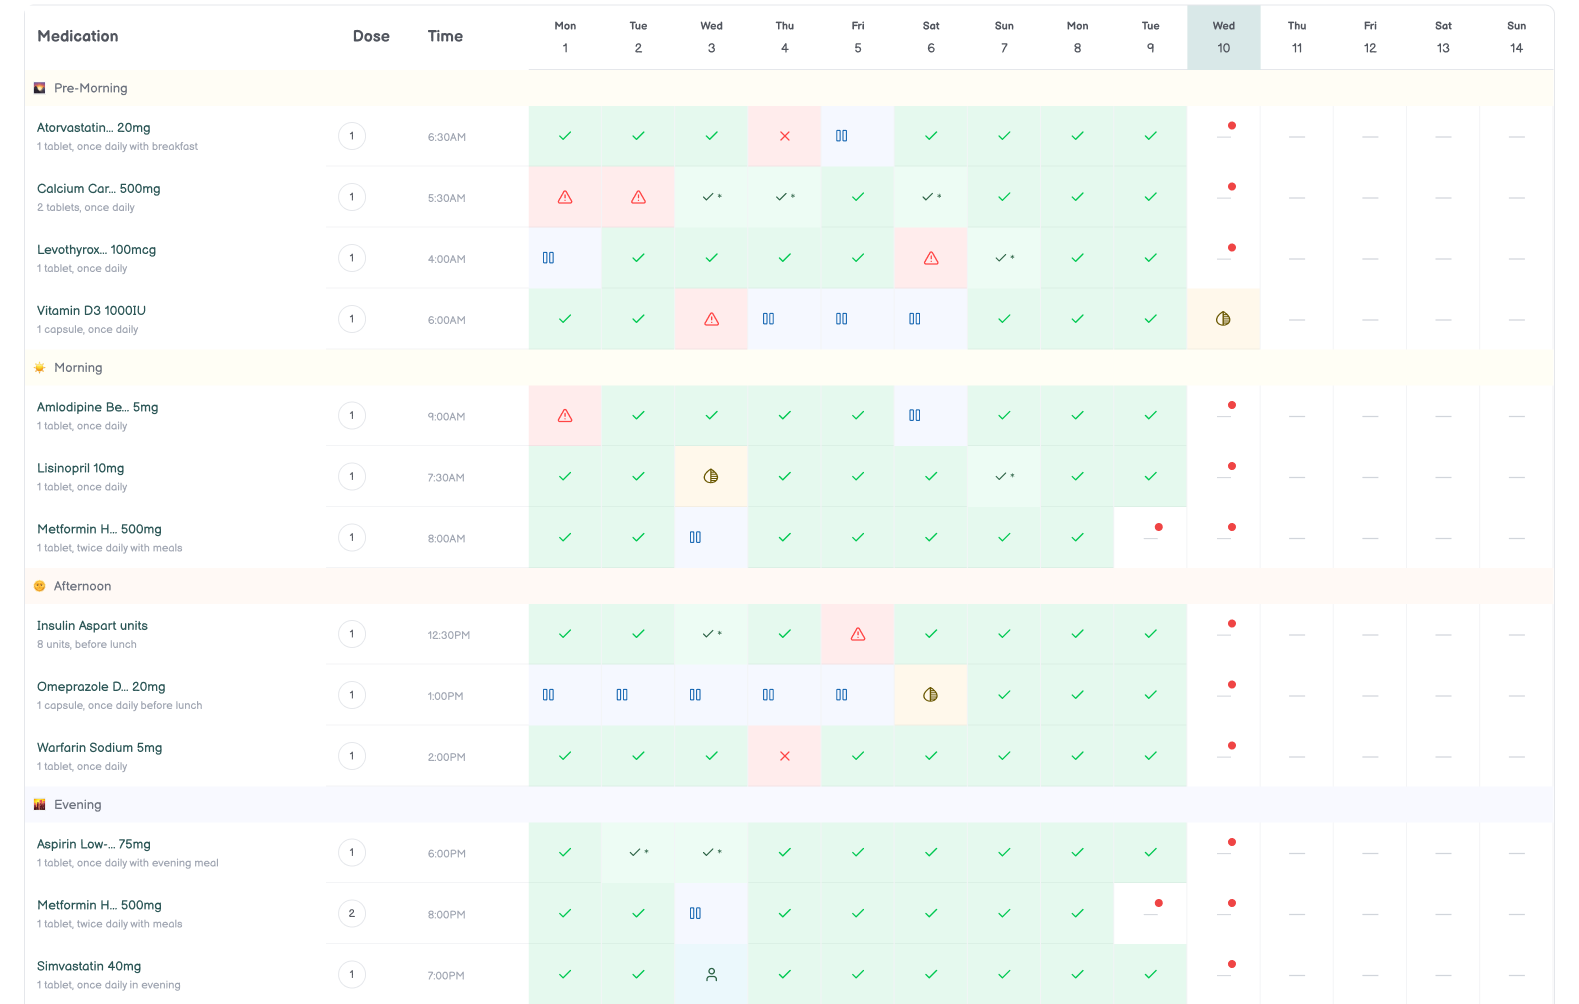
Every cell on the chart pairs an icon with its colour, so the status can still be read by someone who can't tell the colours apart. I wrote the handoff rules into the file as annotations, right down to icon sizes.
 (opens full size in a new tab)
Prototyping
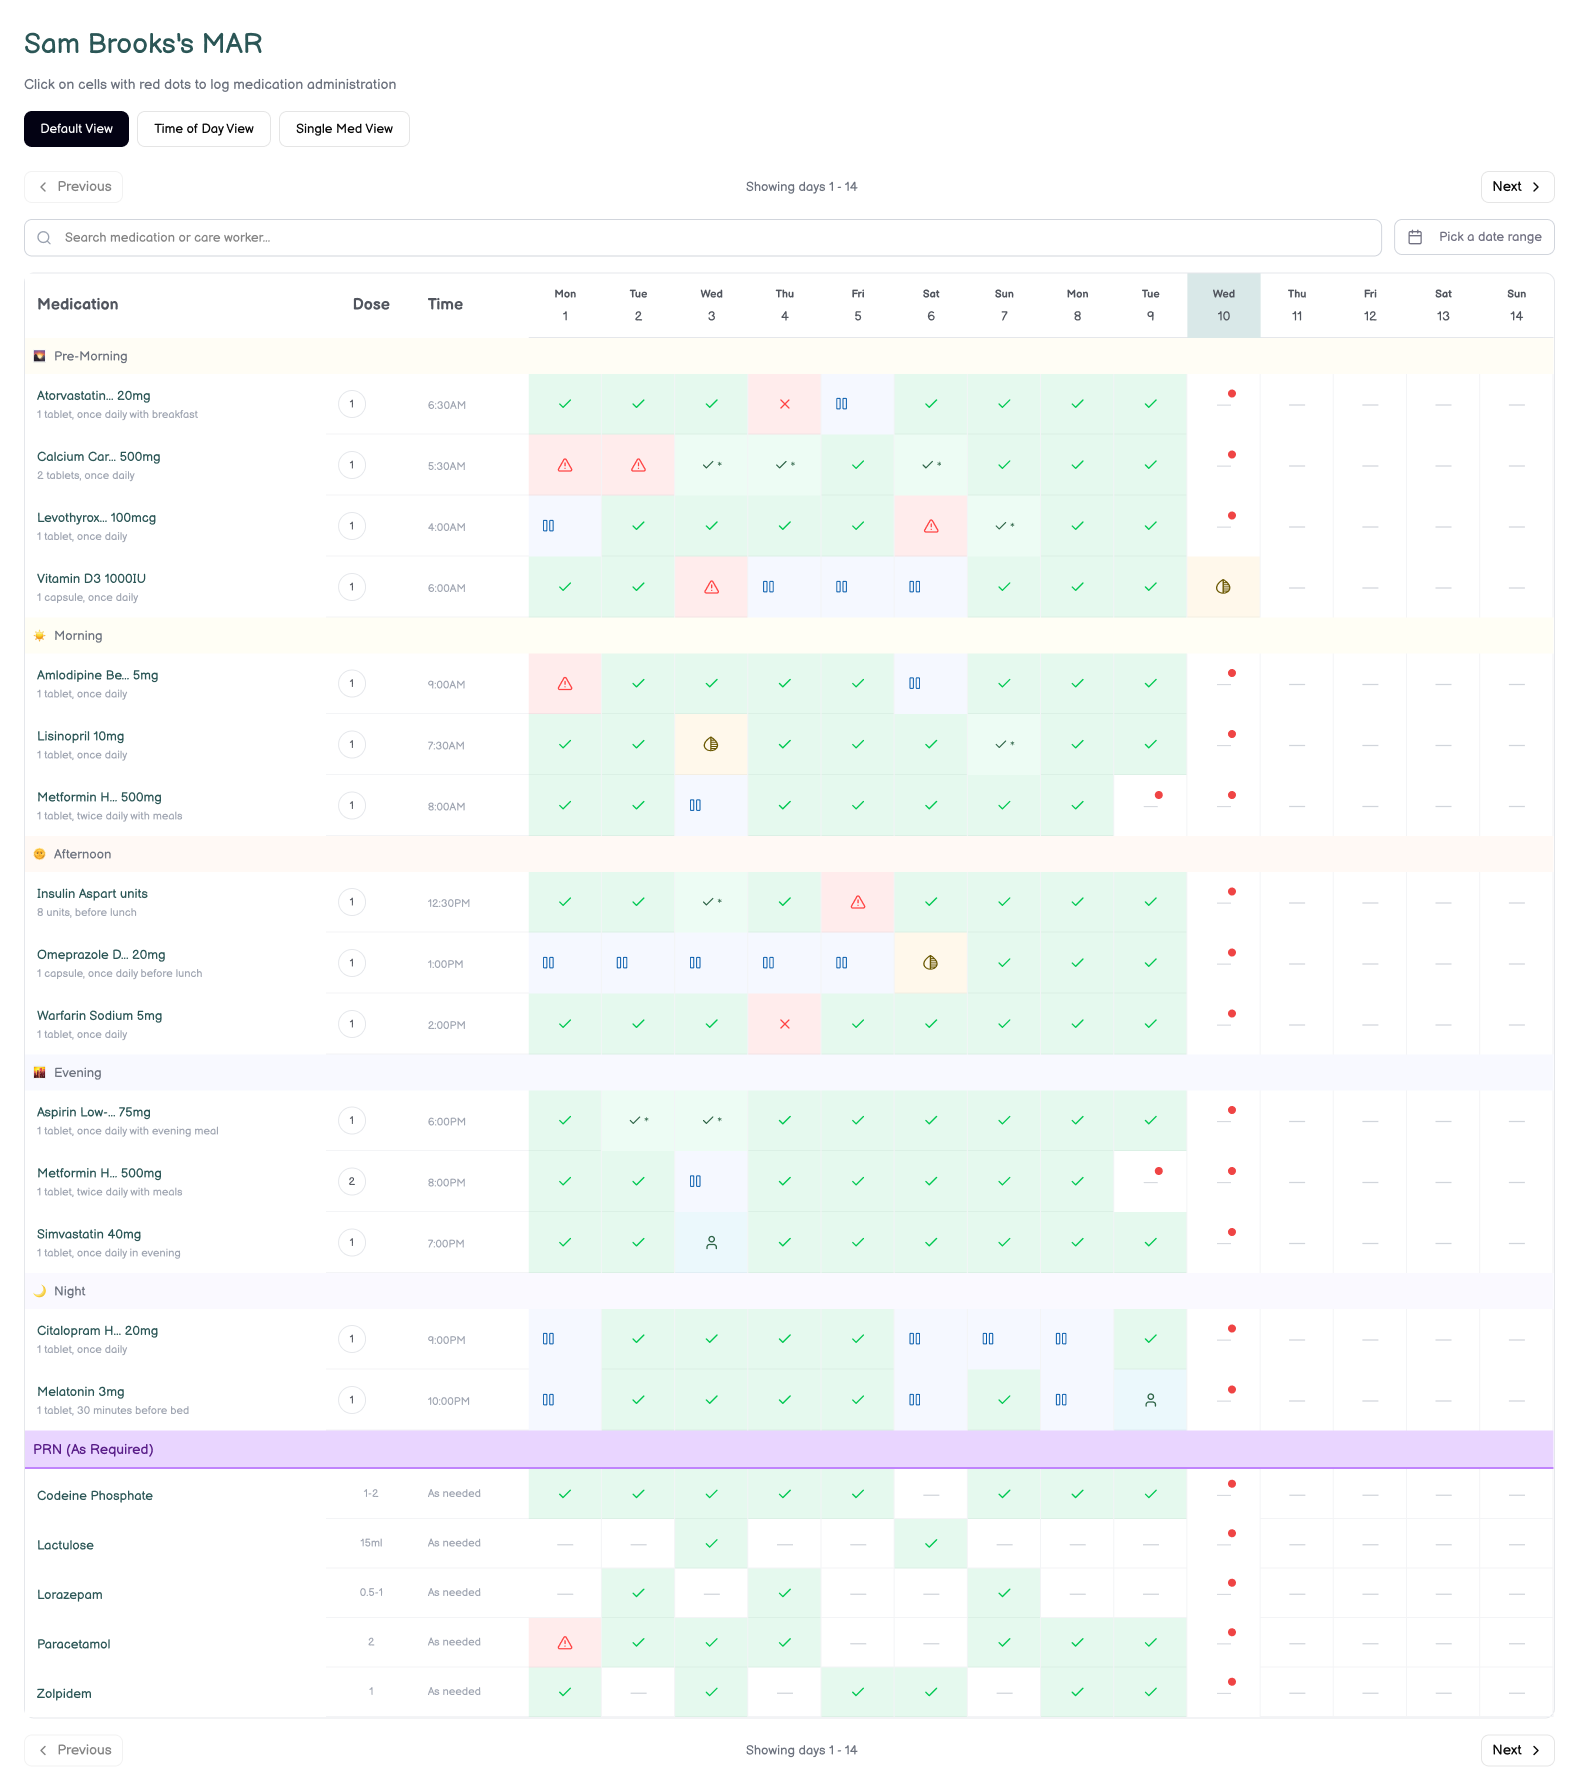
I built a clickable prototype in Figma Make, so stakeholders could use the chart rather than read about it, and so we could take it into user testing. Clinical stakeholders engage with a working prototype in a way they rarely do with a document, and we wanted their pushback whilst changing our minds was still cheap.
Try the clickable prototype (mid-fidelity) →
 (opens full size in a new tab)
Trade-offs
Staying within the regulatory boundary meant leaving out automated interaction checks, dose calculators, and anything that warns or blocks on clinical grounds.
Outcome
We've established a clear, regulation-safe boundary for the work - what the system can support directly, and where clinical judgement has to stay firmly with people. That reframed the whole approach, from a feature list to a model built around managing risk.
The design scope now puts clinical safety first, and sets the stage for user research and testing with more complex prototypes.
Reflection
The constraints ended up being clarifying, as they brought the most difficult questions to the front early on. How do you make the right information visible at the right moment, without the system pretending to decide anything for the person using it?
From this project